Constipation During Pregnancy and Postpartum

Constipation especially during pregnancy can be such a huge problem.  You already feel a lot of pressure, bloating, etc. in your stomach - and now you have a hard time pooping on top of it!  Read on to find out why that happens, and what you can do about it.


What's the deal with constipation during pregnancy?


Constipation during pregnancy is SO common.  In fact, it's the second-most common gastrointestinal disorder during pregnancy behind nausea and vomiting.  11-40% of pregnant people are constipated according to the official diagnostic criteria I outlined in previous articles.  Most of the time, studies report a constipation rate of 30-40% as being most common.  But if you ask pregnant people to self-report symptoms, as many as 61% will say they feel constipated!  And yet, despite its commonness, it's woefully under-studied and under-treated. 


Why do people become constipated during pregnancy?


There are so many contributing factors to the slowing down of your bowels during pregnancy.  I'll provide a laundry list here:

  • high progesterone (especially in the first trimester) slows down gut motility, e.g. the ability of your colon to move your waste through your gut
  • relaxin slows small bowel contractions (peaks at end of first trimester but is present throughout pregnancy)
  • pressure of the pregnant uterus compresses/obstructs the colon in the third trimester
  • decreased physical activity because you feel crappy!
  • hormone changes cause increased water absorption in your colon, leading to hard, lumpy stools
  • medications, such as iron and some anti-nausea/vomiting meds have side effects of constipation
  • fluid loss from vomiting
  • maternal gut microbiome changes
  • reduced fiber and water intake (again, because you feel like crap, and/or have food aversions)
  • rectal pain from hemorrhoids or anal fissures (more on this later)

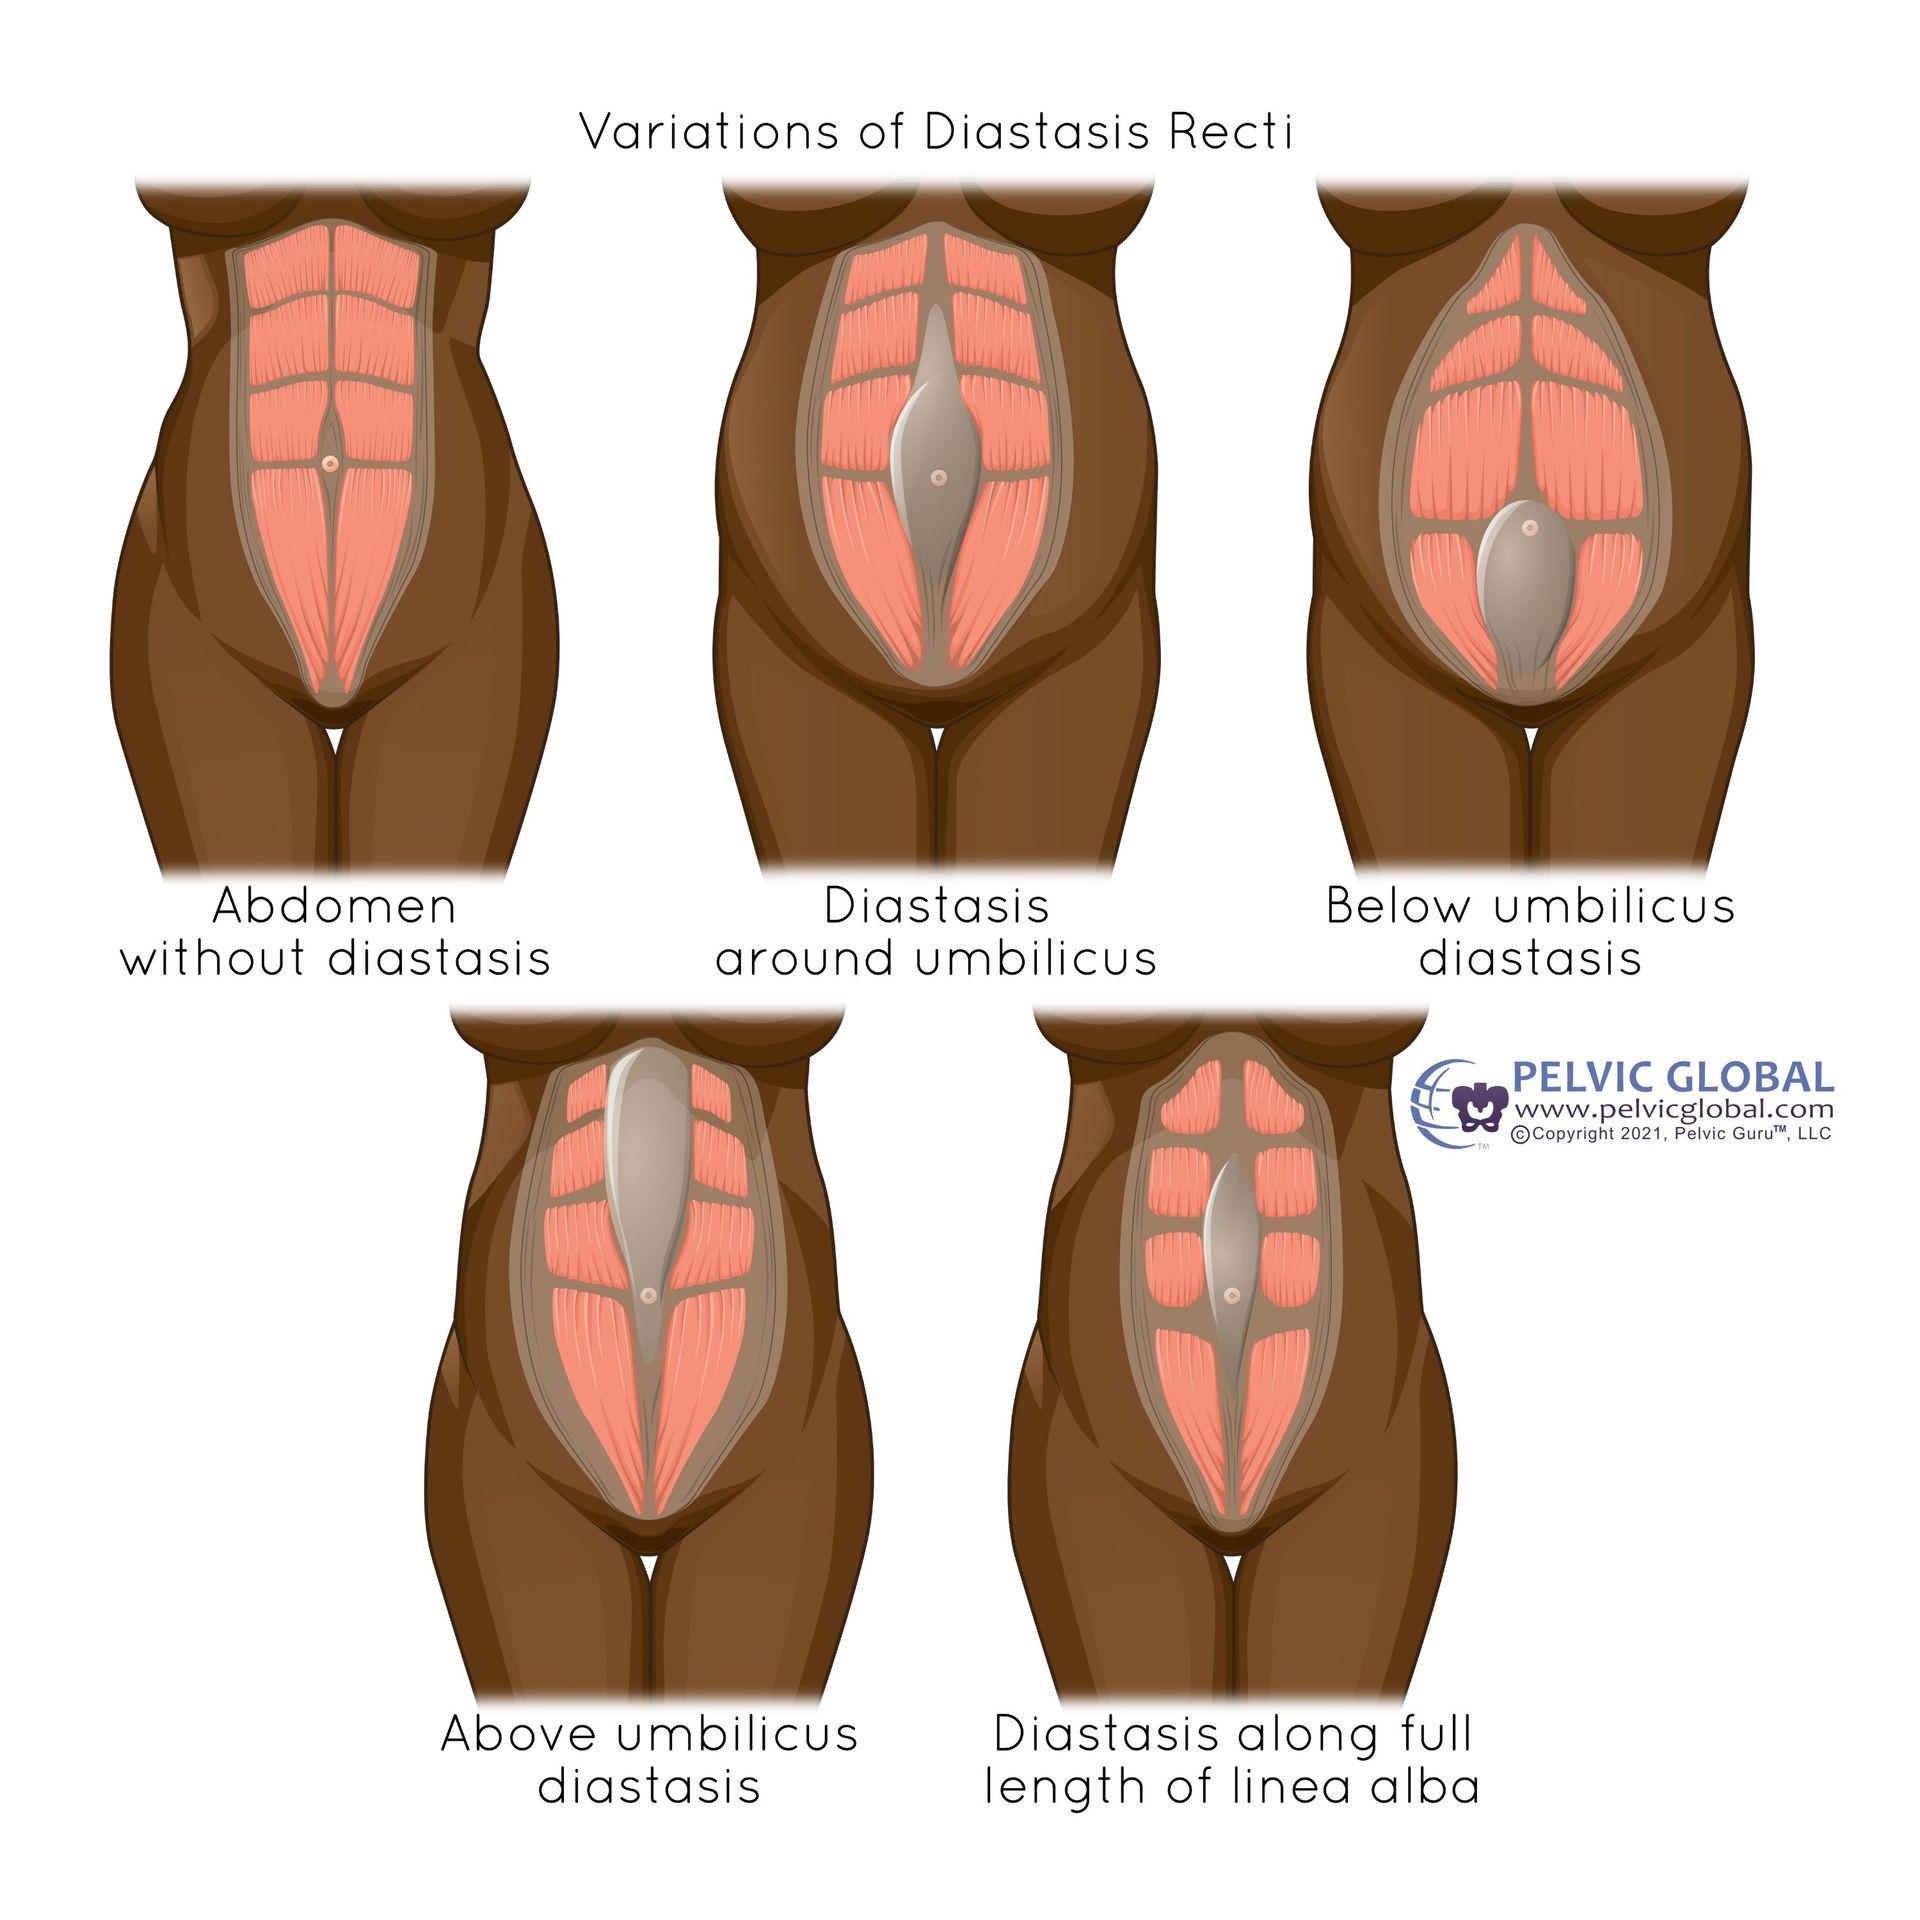
I will also add, although this isn't in the literature, that a growing belly means you can't use your abdominal muscles as effectively to push for your bowel movements (BMs) Plus, we know diastasis rectus abdominis (DRA) is a contributing factor to constipation, and 100% of pregnant people will have a DRA by week 35 of pregnancy.

***************************************************


What are risk factors for constipation in pregnancy?


You are more likely to struggle with constipation while pregnant if any of the following applies to you:

  • decreased physical activity
  • being placed on bedrest
  • low fiber intake
  • decreased fluid intake
  • using iron supplements
  • pre-existing constipation
  • multiple pregnancies
  • previous C-section


Will my doctor order any tests to determine if I am constipated?


Most likely not.  As with most other medical issues during pregnancy, we avoid putting a pregnant body through general medical testing as much as possible to avoid harm to the fetus.  The only exception to this is bloodwork, as your doctor may want to check you for a low thyroid or diabetes.  So, unless you have fecal impaction or have a severe obstruction of your colon, most of the time your doctor will just take your word for it that you are constipated. 


What can I do about constipation in pregnancy?


First, the basics, as always!  Make sure you are moving your body, getting plenty of fluid, and increase your fiber intake to higher than your typical levels.  Of course, this all comes with the caveat that you are likely feeling crappy, so don’t push your body beyond its limits.  Here are some basic recommendations:

  • drink at least 8 glasses of water/day
  • eat 25-40 grams of fiber/day
  • eat smaller, more-frequent meals in the second and third trimesters particularly

I will say though, at least one study does show that increasing fiber and fluid alone is not enough to reduce the symptoms of constipation during pregnancy.  It is likely that the hormonal changes are so strong in the first and second trimesters in particular, that making changes to your diet isn’t enough to overcome the effects of these hormones.  However, this same study did show that low fiber intake was linked to worse pregnancy outcomes.  Specifically it was linked to C-section deliveries, prematurity, and/or fetal growth restriction.  We do know that high fiber diets can reduce the risk of things such as high blood pressure and diabetes, which in a pregnant person can of course cause negative outcomes for the mom and fetus.  So it is possible that eating a high fiber diet in pregnancy can have benefits beyond your bowels.


And, make sure you know how to sit on the toilet and “push” correctly for bowel movements.  If not, please refresh yourself with my first constipation article!  Small changes like a stool underneath your feet can make a big impact!

Plus, for most people, constipation is worst in the first and second trimesters.  So one thing you can actually look forward to about your third trimester is possibly being less constipated! 


If I’m good on fiber and fluid, what’s next?

As I said above, many times just upping fiber and water isn’t enough.  The good news is that many of the same over-the-counter laxatives you can take when not pregnant are also safe for pregnancy.  However, I will say that in general studies on supplements and medications in pregnancy are very sparse.  The data that is there generally is of low quality with a high risk of bias.  So, every person needs to talk to their OB/midwife, and weigh the benefits vs the risks of taking supplements or laxatives in their own bodies. 

Here’s a run-down of some options:


  • Fiber supplements, aka bulk-forming laxatives: psyllium (Metamucil, or you can take this in pill form as psyllium husk), methylcellulose (Citracel), guar, calcium polycarbophil, pectin, and flax seed (ground or whole) are all generally safe and often effective in pregnancy.  Fiber supplements do seem to be effective as compared to no intervention at increasing stool softness and frequency in pregnancy.  However, stimulant laxatives are more effective than fiber supplements, but come with the risk of abdominal discomfort and diarrhea.  And as always, if you are adding in fiber, do so slowly as too much in a short period of time can cause increased bloating and gas.
  • Osmotic laxatives: Polyethylene glycol (aka PEG or Miralax), lactulose, sorbitol, and glycerin are all options that are generally safe for pregnancy, as their mechanism of action is drawing more water into the colon.  Osmotic laxatives are not well-absorbed by the intestine, so very little is absorbed into your bloodstream and thus not passed to the fetus.  However, saline hyperosmotic laxatives are best to be avoided in pregnancy, as they can result in fluid retention.
  • Lubricants: the use of mineral oil and castor oil is best avoided in pregnancy as it can lead to reduced absorption of certain vitamins, and cause premature uterine contractions.
  • Stimulant laxatives: These can be a reasonable option if fiber and osmotic laxatives don’t do the trick.  Senna and bisacodyl are the most common ones, and are minimally absorbed into your bloodstream.  However, senna in particular has been linked to reports of fetal death at higher doses (4%) and has conflicting safety data.  It also may cause an electrolyte imbalance if it ends up causing you diarrhea.  And as I alluded to above, these work by causing intestinal cramping and so sometimes are not well-tolerated.
  • Stool softeners: Ducosate sodium, also known as Colace, is typically the first thing that is recommended by doctors for pregnant people.  However, it’s well-known that ducosate sodium is found to be no better than placebo in very large, high-quality studies of the general population.  So unfortunately, there really is no evidence to show that it works for anyone, regardless of pregnancy status.  But since it’s generally well-tolerated without side effects, it is commonly recommended even though the evidence doesn’t support its use.  I will say though, if you think it’s working for you, don’t stop it just because of this information!  If you stop it and your constipation gets worse, definitely continue.  But if you stop it and you don’t notice a change, you are best off trying something different.


What about postpartum constipation, and that typically-awful first bowel movement after delivery?


Ugh, that first BM after having a baby can be the. worst.  This is regardless of delivery mode, because if you have a vaginal delivery (especially with tearing), the thought of pushing anything else out down there is terrifying!  This is especially true if you are worried about tearing stitches.  And for my C-section moms, your abdominal pain is so great that having to use those abdominals to push or create any force is pretty awful.  Plus, pain makes your muscles tighten up, so even just trying to relax your pelvic floor to get your stool out is a tall ask.


The tough part about answering this question is that the evidence is VERY poor.  A Cochrane review from 2020 only found 5 studies to review, and 4 of them were completed over 40 years ago.  Which means also some of them studied supplements or drugs that we no longer think are safe for people who breast or chest feed.  And the trials that were left are so small and the evidence so poor that really no great conclusions can be drawn from them.

I will say that especially for a vaginal delivery, if you try what is called “splinting” of your perineum, this may help.  You take your fingers, or a wad of tissue paper, and push “upwards” slightly towards your head on your perineum (aka the area between your vagina and rectum). This can provide support to sore/lengthen/torn tissues, and give you some counterpressure to the “push” for the BM. 


Additionally, the basics are KEY here.  Lots of diaphragmatic breathing, relaxation, feet on a stool, and water/fiber to make your stool as soft as possible can be incredibly helpful.


Still have questions or need a little extra help with your bowel health?


Pelvic Love Physio PTs are your local experts in all problems related to the pelvic floor! Please call or text us today at 309-431-1357 and we will be happy to answer all of your questions.


References:


Nagaich, N., Sharma, R., & Nair, N. Gastrointestinal Diseases in Pregnancy; Diagnosis and Management. Gastro Med Res. 2(4). GMR.000544. 2019. DOI: 10.31031/GMR.2019.02.000544 

Rao, S. S. C., Qureshi, W. A., Yan, Y., & Johnson, D. A. (2022). Constipation, Hemorrhoids, and Anorectal Disorders in Pregnancy. The American journal of gastroenterology, 117(10S), 16–25. https://doi.org/10.14309/ajg.0000000000001962

Turawa, E. B., Musekiwa, A., & Rohwer, A. C. (2020). Interventions for preventing postpartum constipation. The Cochrane database of systematic reviews, 8(8), CD011625. https://doi.org/10.1002/14651858.CD011625.pub3


By Stephanie Dillon • September 16, 2026
Treatment of Functional Constipation
By Stephanie Dillon • September 10, 2026
Functional Constipation: Types and Diagnosis 
By Stephanie Dillon • September 1, 2026
Constipation
By Stephanie Dillon • March 31, 2026
Surgery for Diastasis Rectus Abdominis
By Stephanie Dillon • March 31, 2026
What if exercise alone isn't enough to heal DRA?
By Stephanie Dillon • March 31, 2026
What makes you more likely to have DRA?
signs you need pelvic floor therapy
By Stephanie Dillon • March 26, 2026
What are the best exercises for postpartum diastasis rectus abdominis (DRA)?
By Stephanie Dillon • March 26, 2026
What is Diastasis Rectus Abdominis? Aka DR/DRA/Di-recti?
By Stephanie Dillon • January 20, 2025
Prolapse Surgeries, Part II This article is a follow-up to a Part 1 article I wrote on prolapse surgeries, where I covered a lot of FAQs about who needs surgery and why. In this article, we'll cover the nitty gritty of surgeries, including the different types of surgeries and recovery times, etc. We won't rehash what I mentioned last time, so if you have questions about who might need surgery, and how successful surgery generally is or isn't, please revisit the past article! What types of prolapse surgeries are there? There are two types of surgeries. For most people who are patients at Pelvic Love and who are reading this article, they will have a type of surgery that preserves the ability to have vaginal intercourse. There is another type of surgery that closes off the vagina, but then of course after that, you are no longer able to have intercourse. So that is typically reserved for elderly people with vaginas, as this type of surgery has the highest cure rate for prolapse. But of the types of surgeries that leave the vaginal canal open, there are many options depending upon the type of prolapse. Does surgery vary based on the type of prolapse? Yes! For bladder prolapse, the most common type of surgery is called anterior colporrhaphy . In this procedure, the front wall of the vagina underneath the bladder has sutures placed in it to help reinforce the original position of the bladder. For rectocele (rectal prolapse into the vagina), the most common type of surgery is a posterior colporrhaphy . This also involves placing sutures on the backside of the vaginal wall to help keep the rectum in place. Sometimes this is also done in combination with a repair of the perineal body (the area between the vagina and anus), aka perineorrhaphy. What about uterine/cervical prolapse? This gets a little tricky. Many times, if you are done having children and your prolapse is more advanced, you may be advised to have a hysterectomy . However, there are other options that will allow you to keep your uterus. These surgeries are a little more complicated to explain, but if you click this link , you'll find them explained well. Basically they all involve some method of re-suspending the uterus and the cervix by using either stitches or mesh (NOT the mesh that is involved in so many lawsuits!). If you do opt to have a hysterectomy, then as you may imagine, this can place you at a higher risk of bladder and/or bowel prolapsing (if they have not already done so). The uterus takes up a fair amount of space inside the pelvis, so if you remove it, that leaves empty space for other organs to fall into. If I do have a hysterectomy, what are my options to avoid future issues with prolapse? This is the one topic for which I will drag out my soapbox. If you do have a hysterectomy, and it is an option for you, I would HIGHLY recommend your surgeon re-suspends the vaginal vault as part of your surgery . The vaginal vault is the apex of the vagina, and where the vagina is sewn shut after the uterus/cervix is removed. Many surgeons will just stop here and allow the top of the vagina to essentially scar in place. However, as you can imagine, when you remove a major internal organ, then you are also removing (or slackening) a lot of ligaments & fascia that support that organ and others! So this places the top of the vagina at a much higher risk from prolapsing in the future, and/or the bladder and bowel falling into the vagina. Please note, these "extra" steps to support the top of the vagina during a hysterectomy are not available to everyone . They do require more time under anesthesia, potentially greater skill from your surgeon, and the structures the vaginal vault is being sutured to are still intact. For example, I had a friend that had severe endometriosis and had a hysterectomy at 40 years old as a result. Her endometriosis was so advanced, and so many lesions had to be removed from inside the pelvis, that this didn't leave her surgeon with an option for a good place to suspend her vaginal vault. So even though I would recommend you discuss this with your surgeon, it's not an option for everyone. What are the options for suspending the vaginal vault after hysterectomy? There are many places from which the vaginal vault can be suspended after the uterus/cervix are removed. There are too many to go into detail in this format, but all have their pluses and minuses. The main options are the uterosacral ligament , sacrospinous ligament , and the sacrum itself . More general information can be found in this handout . What is recovery like after these types of surgeries? Every surgeon is different, but here are some general guidelines for recovering from a hysterectomy or prolapse repair. And YES, many times there is more than one repair being done at a time! Or a hysterectomy may be combined with an anterior and/or posterior vaginal wall repair, for example. Most often, you will have a catheter in place for anywhere from 8-24 hours after surgery (potentially longer for a bladder repair). And generally, your hospital stay is very short. Typically you need to take anywhere from 2-6 weeks off work. Around 2-3 weeks you can resume driving and taking short walks. And no sex (vaginal penetration) is allowed for 6 weeks. It's also important to remember that because these are very delicate tissues, they are not fully healed for THREE MONTHS. So, for quite some time you will likely have restrictions on heavy lifting. Have even more questions about your pelvic floor in general, or prolapse specifically? Here are two great websites for more info on all kinds of pelvic floor-related issues, not just prolapse: International Urogynecological Association handouts American Urogynecologic Society fact sheets References: All information contained in this post is aggregated from the handouts linked throughout the text.
By Stephanie Dillon • January 20, 2025
Prolapse Surgeries, Part I Whew, surgery for prolapse is a big topic. So much so that I'm splitting it into two articles to avoid overloading your eyeballs and brains! Today we'll spend time discussing the whys and who's surrounding surgery. Then next time we'll get into the details of types of surgeries, recovery times, etc. If I have prolapse, do I definitely need surgery? In a word, no. Or at least, most likely not. I wanted to get this question out of the way first, because I think prolapse can be a very scary diagnosis when you are first told you have it. Then, your brain (or at least mine!) jumps to the most extreme outcome, which would be surgery. As we discussed in a past article about the best exercises for prolapse, pelvic floor muscle training and core strengthening can be a really effective treatment for prolapse. It can relieve your symptoms, delay/prevent the need for surgery, and potentially even reduce the grade of your prolapse. Plus, pessaries are another great non-surgical option that can prevent or delay the need for surgery too (if the idea of a pessary is new to you, check out my past article on pessaries). So, especially if you are newly diagnosed with prolapse, don't jump to the thought that you will have to have surgery someday! Who does need surgery for prolapse? Indications for prolapse surgery are the following: Significant "bother" of symptoms (vaginal heaviness/pressure, associated bowel/bladder symptoms, difficulty/pain with intercourse, etc) "Failed" a good trial of conservative treatment - PT/pelvic floor muscle training, pessaries, etc. that does not satisfactorily resolve symptoms Completed childbearing Typically more-advanced prolapse grades (3-4), unless with lesser grades the symptoms are severe and not responding to conservative treatment If your prolapse is mild (grade 1-2), you are going to have more children, or have other medical conditions that would make surgery difficult, then you can/should avoid it! Typically the biggest differentiator regarding the need for surgery is if the prolapse extends beyond the hymen, or external to the vagina. Conservative treatment is less likely to be successful (but not always, of course!) in cases where the prolapse is external to the vaginal opening. More often than not, surgery will eventually be needed to resolve symptoms. But, that doesn’t mean a good trial of conservative treatment isn’t a good idea! How common is prolapse surgery? It is pretty common, at least with age. If you have a uterus/vagina, you have a lifetime risk of 11-20% of undergoing surgery for prolapse or stress incontinence. By age 80 the risk is 20%. How successful is prolapse surgery? It is very successful, especially in the short term! Success rates are generally around 80-90%, especially within the first 2 years following surgery. However, it is true generally that the further away you get from surgery, the more likely your prolapse may return. And we don't have a lot of high-quality studies that follow people after prolapse surgeries beyond 2 years (many stop around 6-12 months). The other caveat here is how we define "success." There is a BIG difference between restoring your anatomy (i.e., reducing the organ back to its original position, and having it stay there) and improving your symptoms. Around 5 years post-op, the majority of repairs will have "failed" in terms of anatomy. Meaning that if someone did a vaginal examination, the prolapse will have returned (although potentially not to the same degree that it was present before). However, even in these cases, the symptoms are still reported to be much better, and happiness with surgery outcomes is still high. So this is further proof that the degree of prolapse isn’t always equal to the severity of symptoms and that more research is definitely needed. Why do prolapse surgeries fail? There are a lot of reasons. The biggest one is that the tissues surgeons are trying to repair are very delicate. There's a really fine line between suspending an organ via it's own ligaments, or using mesh, with just enough tension vs. using too much tension. So it's always a balance between fixing the original problem without causing further complications. The other is that many times, the original cause of the prolapse has not been corrected. As I discussed at length in my intra-abdominal pressure article, prolapse really is a top-down problem more than a bottom-up problem. In fact, one recent study that looked at outcomes 5 years after prolapse surgery found no difference between those who did and did not do post-operative pelvic floor muscle training (Jelovsek 2018). Essentially, pelvic floor muscle training did not stop the prolapse from returning. So if you still are doing a lot of heavy lifting, have continued constipation, or are just genetically predisposed to having prolapse, there is a high likelihood it will return because there is still a lot of top-down pressure on your internal organs. It's important to note though, as I stated above, generally, your symptoms still remain improved even if the prolapse itself returns post-operatively. Although of course, some people will need to have a second surgery. This is also why it's best to delay surgery for as long as possible. Should I have prolapse surgery? This is obviously a very personal decision, and depends upon a lot of factors! I think the biggest takeaways here are that you should try PT, pelvic floor & core exercises, and/or pessaries first. Pelvic Love also fits in well with these exercise recommendations, and has some specific videos for prolapse! All of these things are recommended to be the first-line interventions for prolapse and can help the majority of people who are living with prolapse. If that doesn't work for you, or for whatever reason your surgeon determines surgery is the best route right away, then definitely consider it.  It can be very successful, especially for symptom improvement! As with any surgery though, I would always recommend getting at least 2 opinions before deciding to move forward. And I would highly recommend at least one of those opinions come from a urogynecologist or colorectal surgeon depending upon your needs. The next article will discuss different options for prolapse surgeries, so be sure to check that one out! References: Bureau, M., & Carlson, K. V. (2017). Pelvic organ prolapse: A primer for urologists. Canadian Urological Association journal = Journal de l'Association des urologues du Canada , 11 (6Suppl2), S125–S130. https://doi.org/10.5489/cuaj.4634 Dumoulin, C., Hunter, K. F., Moore, K., Bradley, C. S., Burgio, K. L., Hagen, S., Imamura, M., Thakar, R., Williams, K., & Chambers, T. (2016). Conservative management for female urinary incontinence and pelvic organ prolapse review 2013: Summary of the 5th International Consultation on Incontinence. Neurourology and urodynamics , 35 (1), 15–20. https://doi.org/10.1002/nau.22677 Jelovsek, J. E., Barber, M. D., Brubaker, L., Norton, P., Gantz, M., Richter, H. E., Weidner, A., Menefee, S., Schaffer, J., Pugh, N., Meikle, S., & NICHD Pelvic Floor Disorders Network (2018). Effect of Uterosacral Ligament Suspension vs Sacrospinous Ligament Fixation With or Without Perioperative Behavioral Therapy for Pelvic Organ Vaginal Prolapse on Surgical Outcomes and Prolapse Symptoms at 5 Years in the OPTIMAL Randomized Clinical Trial. JAMA , 319 (15), 1554–1565. https://doi.org/10.1001/jama.2018.2827 Weintraub, A. Y., Glinter, H., & Marcus-Braun, N. (2020). Narrative review of the epidemiology, diagnosis and pathophysiology of pelvic organ prolapse. International braz j urol : official journal of the Brazilian Society of Urology , 46 (1), 5–14. https://doi.org/10.1590/S1677-5538.IBJU.2018.0581